Oct 15, 2026

Author : Dr. Nitu Verma (P.T)

Somebody's neighbour always tells them to blow up balloons.

Or chew gum all day, or pull the biggest grimace they can manage in front of the mirror twenty times an hour. The advice is kindly meant and it can cost a person the shape of their face for the rest of their life. I'll explain exactly why further down, because that explanation is the most useful thing in this article.
But first, the order of events, because order matters more here than in almost anything else I treat. Bell's palsy treatment in Raipur begins with a doctor on day one, not with a physiotherapist and not with a neighbour.
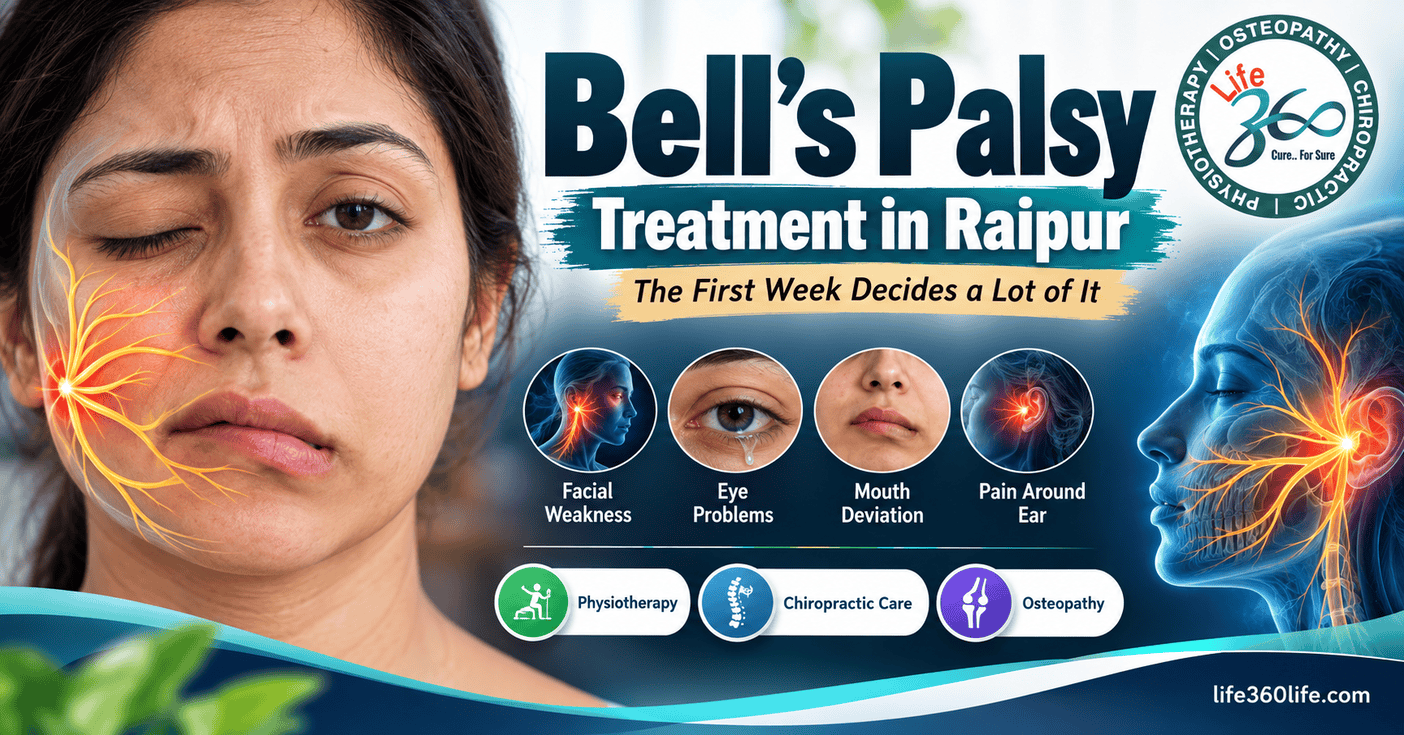
You wake and half your face won't move. The eye won't shut. Water runs out of the corner of your mouth when you drink. Your smile pulls sideways. The first thought, every single time, is stroke.
Any sudden facial weakness needs urgent assessment by a doctor, today, to tell Bell's palsy apart from a stroke. Do not wait to see if it settles, and do not come to a physiotherapist first.
And if it is Bell's palsy, the outlook is generally good. What you do in the first few days genuinely changes where you end up.

Is it Bell's palsy or a stroke?

In Bell's palsy the forehead is involved and the eye will not close. In facial weakness from a stroke the forehead is usually spared. Clinicians use that one quick distinction and it's worth you knowing it.
In Bell's palsy, you can't raise the eyebrow or wrinkle the forehead on that side, and you can't close the eye properly.
In facial weakness from a stroke, the eyebrow still lifts and the eye still closes, while the lower face droops.
The reason is anatomical. Your forehead muscles get nerve supply from both sides of the brain, so a one-sided lesion in the brain leaves them working. Bell's palsy hits the facial nerve itself, after it has left the brainstem, so everything that nerve supplies goes down with it, forehead included.
This test is a guide. It is not a diagnosis. Sudden arm or leg weakness, difficulty speaking, a sudden severe headache, loss of vision, or confusion mean emergency assessment no matter what the forehead is doing. If you're unsure, treat it as an emergency. Nobody has ever been harmed by going to hospital and being sent home relieved.

What is Bell's palsy?

Sudden weakness or complete paralysis of the muscles on one side of the face, from dysfunction of the seventh cranial nerve. Patients usually describe it as one-sided facial droop or mouth deviation.
The facial nerve runs through a narrow bony canal in the skull. The thinking is that inflammation and swelling of the nerve inside that tight space, commonly linked to viral reactivation, compresses it and stops it working properly.
It's called idiopathic, which is medicine's honest way of saying that in most individual cases nobody identifies the trigger. I can't tell you why it picked you. Neither can anyone else.
Onset is fast. Weakness usually reaches its worst within 48 to 72 hours. Facial weakness that creeps in slowly over weeks is not typical of Bell's palsy and needs investigating for other causes.

What people notice

  • Sudden one-sided facial weakness, or complete paralysis
  • The eye won't close on that side, or won't close fully
  • The corner of the mouth droops, and you drool
  • The nasolabial fold, the line from nose to mouth corner, disappears on that side
  • Eating and drinking get difficult, and food collects in the cheek
  • Speech is affected, especially sounds that need the lips to meet
  • Taste changes on the front of the tongue
  • Sound becomes uncomfortably loud on that side
  • Pain behind or around the ear, often arriving a day or two before the weakness
  • Less tear production, or an eye that streams
  • A feeling of numbness in the face, though sensation usually tests normal

What should I do in the first 72 hours?

See a doctor. Today. Corticosteroid treatment started inside the first 72 hours is the single most time-sensitive part of facial nerve treatment.
Partly to exclude stroke and other causes. And partly because corticosteroid treatment started early is the mainstay of medical management for Bell's palsy. The evidence supports starting steroids inside the first 72 hours, and sooner is better than later within that window. Antivirals may be added in some cases, at the doctor's discretion.
This is time-sensitive in a way most of what I treat is not. Somebody in Raipur who waits a week to see whether it improves on its own has spent the window when medication does the most good.

Protecting the eye

If your eye can't close fully, the cornea is exposed and unprotected, and this is the most urgent piece of self-care in the whole condition.
Your blink reflex is what spreads tears across the surface of the eye, and it isn't working. Corneal drying, ulceration and lasting damage to vision are real risks, and they can develop fast.
So:
  • Lubricating eye drops, used frequently through the day, as your doctor advises
  • A thicker ointment at night
  • Tape the eyelid closed at night, or use an eye patch, following medical advice on how to do it
  • Sunglasses outdoors, against dust, wind and sun. In Raipur, through the dry and dusty months, this matters more than it would elsewhere
  • Any eye pain, redness or change in vision means immediate ophthalmology review
Eye protection is not a minor detail and it is not optional. Of everything in this article, this is the part I would want you to act on within the hour.

Should I do strong facial exercises for Bell's palsy?

No. Forceful, high-effort exercise during the regeneration period goes with worse synkinesis, and the damage it causes can be permanent. Small, precise, mirror-guided movement is what the nerve needs.
Back to the balloons.
The instinct of patients, and of some practitioners who ought to know better, is to work the paralysed muscles hard. Forced grimacing. Constant chewing gum. Blowing up balloons. Strong electrical stimulation. Vigorous facial massage.
The trouble is what happens while the nerve regrows.
Facial nerve fibres regenerate slowly, and they don't reliably find their way back to where they started. Fibres meant for the mouth can end up supplying muscles around the eye, and the other way round. When that happens you get synkinesis, which means unwanted linked movement. The classic version is the eye narrowing every time the person smiles. Or the corner of the mouth pulling each time they blink.
Synkinesis is hard to treat once it's established, and for a lot of people it stays as a permanent cosmetic and functional problem.
What the nerve needs while it's finding its way is small, precise, controlled movement, done in front of a mirror, with all the attention on quality and isolation rather than on effort.
The rule I give people: slow, small, symmetrical, and in front of a mirror.
Patients don't like this rule. They want to be doing something vigorous, because their face has stopped working and sitting still feels like giving up. I understand it completely and I still say no.
What I can't predict is who will get synkinesis and who won't. I've seen careful patients develop it and careless ones escape it. The exercise approach shifts the odds. It doesn't hand out guarantees, and I won't pretend otherwise.

How treatment is staged here

What helps in week one is different from what helps in month four, so the programme changes as you do.
In the acute phase, roughly the first two to three weeks, the work is education about the condition and what to realistically expect, eye care instruction and support, gentle massage for comfort and circulation, passive support of the facial tissues, and an assessment of the neck and posture, because compensatory tension is very common. And the deliberate absence of forceful exercise. Doing less is the active ingredient at this stage.
As movement starts returning, we move to mirror-based facial retraining. Facial retraining exercises here mean small, isolated movements practised precisely. Learning to move one region of the face without dragging the rest of it along. Relaxing the unaffected side, which tends to overwork and haul the whole face across towards it, something patients rarely notice until it's pointed out. Then functional practice with eating, drinking and speaking. Mouth deviation treatment sits in this stage, and it works through control rather than through force.
Later, if synkinesis has developed, the work becomes specific retraining to inhibit those linked movements, gentle manual therapy for tight facial muscles, and relaxation techniques. Where the synkinesis is marked, I'll refer you for a specialist opinion, because there are further medical options that sit outside what physiotherapy does.
I don't use electrical stimulation on these faces. Its use is debated, it isn't universally recommended, and there are concerns about it contributing to synkinesis. Plenty of clinics still offer it. You're free to disagree with me on this one, but that's my position and I'll tell you the reasoning at the first visit.

How long does Bell's palsy take to recover?

Improvement typically starts within two to three weeks and carries on over three to six months, and some people keep improving right up to a year. Most people recover well and the large majority recover completely.
A smaller number are left with some residual weakness or some synkinesis.
Better outcomes go with incomplete rather than complete paralysis at the start, early steroid treatment, younger age, and early signs of movement returning.
If nothing at all has improved after three to four months, that needs further investigation and a fresh look at the diagnosis. Other causes of facial weakness exist, including tumours, Ramsay Hunt syndrome, Lyme disease and problems in the middle ear.

Getting through the months in between

Eat slowly and in smaller mouthfuls, and know that food will collect in the affected cheek without you feeling it. Use a straw if drinking is a struggle. Chew on the unaffected side. Keep the eye protection going every single day, at night and outdoors, on the days you feel better as much as the days you don't. Rest, because the fatigue is real and the sheer effort of speaking and eating is real.
And the part nobody warns people about. A visibly changed face hits your confidence hard. People stop going to work, stop meeting friends, stop being photographed. That's not vanity and it isn't weakness, it's a normal response to something distressing happening to the part of you that faces the world. If you're finding it difficult, you're responding the way most people respond.

Where can I get Bell's palsy treatment in Raipur?

Dr. Nitu Verma (PT) provides facial palsy rehabilitation at Life 360 Physiotherapy Center in Shankar Nagar, Raipur. I trained as a physiotherapist first and went on to study chiropractic and osteopathy.
Facial palsy treatment in Raipur here is staged and it is cautious, with eye protection and precise retraining ahead of the aggressive exercise that risks permanent synkinesis. We work alongside your treating doctor. And when what you need is a medical or ophthalmology review rather than a physiotherapy session, I'll say so plainly.
Anyone comparing clinics for the best physiotherapy for Bell's palsy Raipur offers should ask one question: will you use strong electrical stimulation and forced grimacing. The answer tells you most of what you need to know.

Booking facial rehabilitation

If you've had sudden facial weakness, see a doctor today. Once you've had medical assessment and the diagnosis is settled, structured facial paralysis physiotherapy in Raipur gives you the best chance of a full recovery.
Life 360 Physiotherapy Center
HIG-16, Sector 1, Shankar Nagar, Raipur, Chhattisgarh 492007
Also at Life360 Chiropractic Centre, Smriti Nagar, Bhilai
Bring your prescription and any specialist notes. Dr. Nitu Verma (PT) sees facial palsy patients at Life 360 Physiotherapy Center, Shankar Nagar, Raipur.

Questions patients ask

How do I know if it's Bell's palsy or a stroke?
In Bell's palsy the forehead is affected and the eye can't close. In facial weakness from a stroke, the forehead is usually spared. This is a guide only. Any sudden facial weakness needs urgent medical assessment, above all alongside limb weakness or difficulty speaking.
How quickly should treatment start?
Medical assessment should be immediate. Corticosteroid treatment works best when started within the first 72 hours of onset, so a delay directly costs you.
Will my face fully recover?
The large majority of people with Bell's palsy recover completely. Recovery generally begins within two to three weeks and continues over three to six months.
Which Bell's palsy exercises should I do?
Small, precise, mirror-guided movements that isolate one region of the face at a time. Not forceful grimacing and not heavy resistance. Aggressive exercise while the nerve is regenerating goes with worse synkinesis.
What is synkinesis?
Unwanted linked facial movement, such as the eye narrowing when you smile, caused by regenerating nerve fibres reaching the wrong muscles. It's difficult to reverse, which is why the retraining approach matters so much.
Why must I protect my eye?
Because an eye that can't close isn't being protected by blinking and tear spread. Corneal drying and ulceration can develop quickly and can permanently affect vision. Drops, night ointment, taping and sunglasses are not optional.
Is electrical stimulation useful for Bell's palsy?
Its use is debated and it isn't universally recommended, with concerns about it contributing to synkinesis. Retraining built on precise, controlled voluntary movement has wider support.
When should physiotherapy start?
After the medical assessment, and usually within the first two to three weeks, though the early sessions are mostly eye care, education and gentle work rather than exercise. Starting late costs less than starting with the wrong kind of exercise.
Where do I find a Bell's palsy doctor in Raipur?
A physician or neurologist first, on the day the weakness appears, for the diagnosis and the steroids. Facial rehabilitation follows. Dr. Nitu Verma (PT) provides Bell's palsy treatment in Raipur from Life 360 Physiotherapy Center in Shankar Nagar.
Can Bell's palsy come back?
Recurrence is uncommon but it happens. Repeated episodes, or weakness on both sides of the face, need fuller investigation for an underlying cause.
 
Go to Top